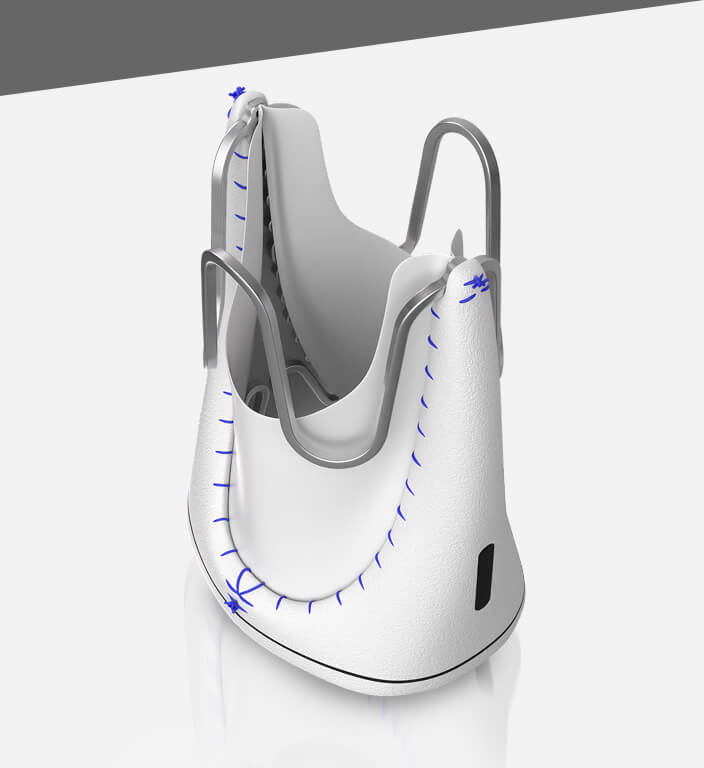
Created specifically for small anatomies
Appropriate for children as small as 10 kg


The only expandable surgical pulmonary valve designed for pediatric patients
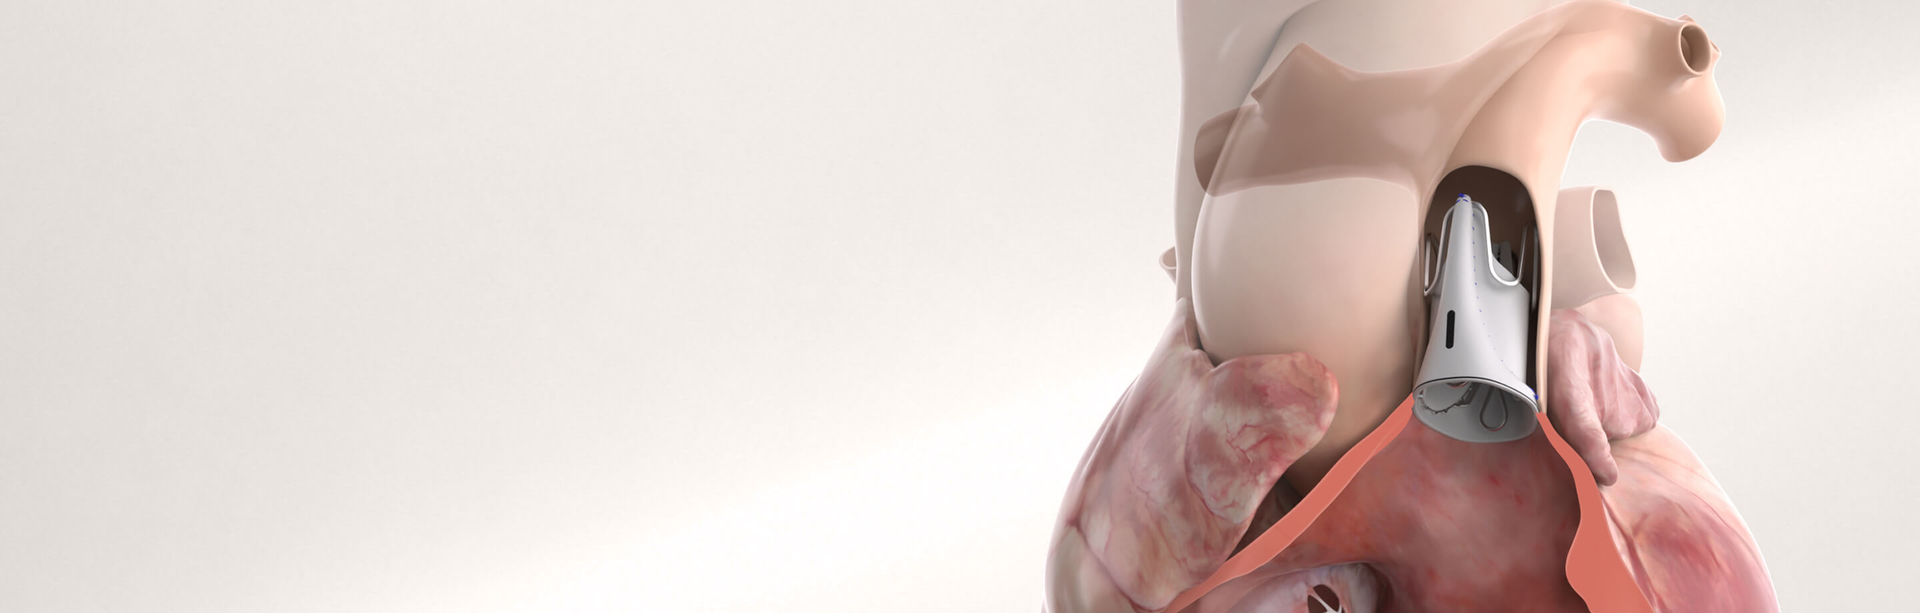
Until now, pediatric patients with pulmonary valve disease (PVD) had limited treatment options, and no solutions that directly meet their unique needs. As a result, they are at greater risk of irreversible right ventricular damage and reduced quality of life.
AUTUS size-adjustable valve is the only expandable surgical pulmonary valve replacement designed to accomodate growing children born with pulmonary valve disease (PVD).1,2 The valve provides a long-term treatment pathway that may preserve right-heart function3 and potentially reduce the burden of future open-heart surgeries.2,4
Early clinical results show benefit to right ventricular function following AUTUS valve implantation3

Appropriate for children as small as 10 kg

At implantation, AUTUS valve is sized to match the body surface area, helping optimize hemodynamic performance

Inspired by the human venous valve, the bileaflet design is made from ePTFE membrane

The valve diameter is expandable to account for somatic growth via transcatheter procedure
Long-term clinical studies are ongoing to evaluate these benefits.
ePTFE=expanded polytetrafluoroethylene
AUTUS Size-Adjustable Valve
Indications: The AUTUS valve is indicated for the management of pediatric patients weighing ≥10 kg who require surgical pulmonary valve replacement for dysfunctional native or surgically-repaired right ventricular outflow tract (RVOT), as determined by echocardiography to meet the following criteria: (1) severe pulmonary stenosis (i.e., right ventricle (RV) to pulmonary artery (PA) peak instantaneous gradient ≥ 60 mmHg); (2) ≥ moderate pulmonary regurgitation;
or (3) ≥ moderate pulmonary stenosis (i.e., RV to PA peak instantaneous gradient ≥ 40 mmHg) and ≥ moderate pulmonary regurgitation.
Contraindications: The AUTUS valve is contraindicated in patients who have active bacterial endocarditis, any other active infection in the heart or body, or have a known intolerance to anticoagulant or antiplatelet drugs (including aspirin).
Warnings: This device is designed, intended, and distributed for single use only. Do not resterilize or reuse this device. There are no data to support the sterility, non‐ pyrogenicity, and functionality of the device after sterile reprocessing. Do not freeze or expose the valve to extreme heat. Exposure of the valve to extreme temperatures will render the device unfit for use. Do not use the valve if the tray/Tyvek lid are opened, damaged, or stained; if the expiration date has elapsed, or if it is dropped, damaged, or mishandled in any way. Should a valve be damaged during insertion, do not attempt repair.
Precautions: Safety and Effectiveness of the AUTUS valve in a non-pulmonary position, including aortic, mitral, or tricuspid valve replacement has not been established. Safety and effectiveness of deploying a transcatheter valve within the AUTUS valve has not been established. There is no non-clinical or clinical data on valve-in-valve procedures with the AUTUS valve. Safety and effectiveness of post-implant expansion of the AUTUS valve has not been established. There is currently limited clinical data on post-implant valve expansion procedures. The total number of expansion procedures that a patient can undergo in a lifetime is unknown. There is presently no clinical experience with more than one expansion procedure being performed for a patient. Do not expose the valve to any solutions, chemicals, antibiotics, etc., except for sterile physiological saline solution. Do not grasp the leaflet material of the valve with instruments or use forceps to manipulate leaflet material. Do not oversize. Oversizing at the time of the implant procedure with or without pre-expansion may cause valve damage or localized mechanical stresses, which may in turn injure the heart or result in leaflet material failure, frame distortion or regurgitation. Do not trim the sleeve/sewing cuff to beyond the most inferior portion of the stent frame (as indicated by black line). Do not attempt balloon dilatation of the AUTUS valve after suturing the valve into the right ventricular outflow tract during the index procedure. Do not attempt to crimp/compress an expanded valve down to a smaller diameter. Do not deform frame when handling device. During pre-implant balloon expansion, do not adjust position of valve with the balloon inflated. Do not position valve in right ventricular outflow tract during implantation such that distal valve is not coaxially aligned within the main pulmonary artery. This can result in the valve being placed under compressive forces from the overlying patch and/or native vessel. Failure to assure correct valve positioning could potentially lead to valve dysfunction, leaflet material damage, frame fracture, vessel/patch erosion or aneurysm formation. During post-implant balloon expansion, do not position wire incorrectly, use an inappropriate balloon length or allow balloon malalignment with frame (specifically, working length of balloon must remain straight throughout full length of device during inflation). Do not inflate balloon beyond nominal pressure during post-implant valve expansion procedure. Clinical long-term durability has not been established for the AUTUS valve. Regular medical follow-up is advised to evaluate valve performance. Cases of valve frame fracture have been observed clinically. There may be limitations with x-ray imaging to confirm fracture events. If frame fracture is suspected, advanced imaging (e.g., fluoroscopy) to evaluate the presence of fractures is recommended when clinically indicated. There is presently no clinical experience with post-implant expansions of fractured valve frames. Limited engineering data suggests that valve frames with fractures at the base of the frame along the leaflet attachment feature (where fractures have been observed clinically) may maintain acceptable valve hydrodynamic performance when expanded. Cases of reduced leaflet mobility have been observed clinically. Patients experiencing impaired leaflet mobility should be followed closely. Advanced imaging to evaluate impaired leaflet mobility is recommended when clinically indicated. There is no clinical experience with post-implant expansions of valves with reduced leaflet mobility. The potential clinical impact of reduced leaflet mobility on the ability to perform post-implant valve expansion is unknown. If leaflet thrombus is suspected, additional imaging, including transesophageal echocardiography or CT imaging should be considered prior to performing a post-implant valve expansion procedure. As with any implanted medical device, there is a potential for patient immunological response to the metal alloys in the device. Care should be exercised in patients with hypersensitivities to such materials.
Potential Adverse Events: Allergic reaction to valve materials or contrast media; annulus damage including dissection, perforation, or tear; atelectasis; aortic damage including dissection, perforation, or tear; bleeding, including peri- or post-procedural, anticoagulant-related, pericardial tamponade, or hematoma; blood related issues, including anemia, coagulopathy, or hemolysis; blood pressure alteration, including hypo- or hypertension; cardiac arrest (asystole); cardiac arrhythmias or conduction disturbances; cardiogenic shock; coronary artery compression; death; deep vein thrombosis; disseminated intravascular coagulation; embolism; esophageal tear/rupture; fever; frame fracture or distortion with or without obstruction or loss of structural integrity; hemolysis; hypoxemia; infection, including endocarditis, local (wound) or systemic; multi‐system organ failure; myocardial infarction; neurologic events, including cerebrovascular accident or transient ischemic attack; pain, swelling, or bruising at the catheterization site; perforation of a major blood vessel or a heart chamber; pericardial effusion; pleural effusion; pneumonia; pneumothorax; prosthetic Insufficiency – regurgitation and/or stenosis; pulmonary artery damage, including dissection, perforation, or tear; pulmonary edema; radiation-induced erythema; reduced exercise tolerance; reduced leaflet mobility; renal failure (RF) or insufficiency, including acute RF and contrast induced nephropathy; respiratory failure; rupture of the RVOT; thrombocytopenia, including heparin-induced thrombocytopenia; thromboembolism, including arterial, venous, peripheral, pulmonary, or central thromboembolism; transvalvular or valvular leaking; valve nonstructural dysfunction, including paravalvular leak, leaflet impingement, leaflet damage (caused by instruments or sutures), pannus, prosthesis mismatch (due to inappropriate sizing, distortion at implant); valve structural dysfunction/deterioration (stenosis or regurgitation); valvular thrombosis.
CAUTION: US law restricts this device to sale by or on the order of a physician. See instructions for use for full prescribing information.
PP--US-13229 v1.0
We are committed to providing your institution, clinicians and staff with the highest levels of customer service and support to ensure seamless product implementation and ongoing use, including:
24/7 Technical support
For product information and orders